Peripheral nerve stimulation
Peripheral nerve stimulation places a hair-thin wire next to one specific nerve outside the spine, in the shoulder, back, knee, foot, or elsewhere, to calm the pain signals coming from it. As with spinal cord stimulation, you try it temporarily before deciding on anything permanent.
- TargetedAims at one nerve or one area
- Trial firstA temporary test before any implant
- Outside the spineThe leads never enter the spinal canal
- OutpatientLocal numbing, sometimes light sedation
What is peripheral nerve stimulation?
Peripheral nerves are the nerves outside the spine. They run through your shoulders, arms, back muscles, hips, legs, and feet. When one of them keeps sending pain signals long after an injury or surgery has healed, a peripheral nerve stimulator (PNS) can help quiet it. A very thin wire, called a lead, is placed next to that nerve. It delivers mild electrical pulses that interfere with the pain signal before it reaches the spinal cord and brain.
PNS is more targeted than a spinal cord stimulator. It treats one nerve or one area rather than a whole region of the body. The leads stay outside the spine, so spine-specific risks such as spinal fluid leaks don’t apply.
There is more than one kind of PNS system
- Wearable-powered systems: a tiny implanted receiver with no internal battery, powered through the skin by a disc you wear. This is the type shown in the illustration below.
- Fully implanted systems: a small battery sits under the skin, similar to a spinal cord stimulator.
- Temporary systems: a lead is used for a set treatment period, often about 60 days, and then removed completely.[4]
Your physician will explain which type is being recommended for you and why.
Is PNS right for me?
PNS is generally considered for severe, long-lasting pain that comes from a specific peripheral nerve, after standard treatments such as physical therapy, medicines, and injections have not given enough relief. One commonly used system is FDA-cleared for “severe intractable chronic pain of peripheral nerve origin”. It is not intended for the head or face.[5]
Often considered for
- Nerve pain that remains after surgery or injury, including around a joint such as the knee or shoulder
- Chronic pain in one area of the low back, shoulder, knee, or foot and ankle[3]
- A pinched or scarred nerve that has not responded to other care
- Pain in a clear nerve pattern (burning, shooting, electric, or hypersensitive to touch)
- People who got strong but short-lived relief from a diagnostic nerve block. That result helps confirm which nerve to target.
May not be a good fit if you have
- Widespread pain in many parts of the body
- Skin infection or a skin condition where the device would go
- A bleeding problem, or blood thinners that cannot safely be paused
- Pregnancy
- Trouble wearing, charging, or using the device consistently
- A problem that surgery or another treatment should address first
How it works
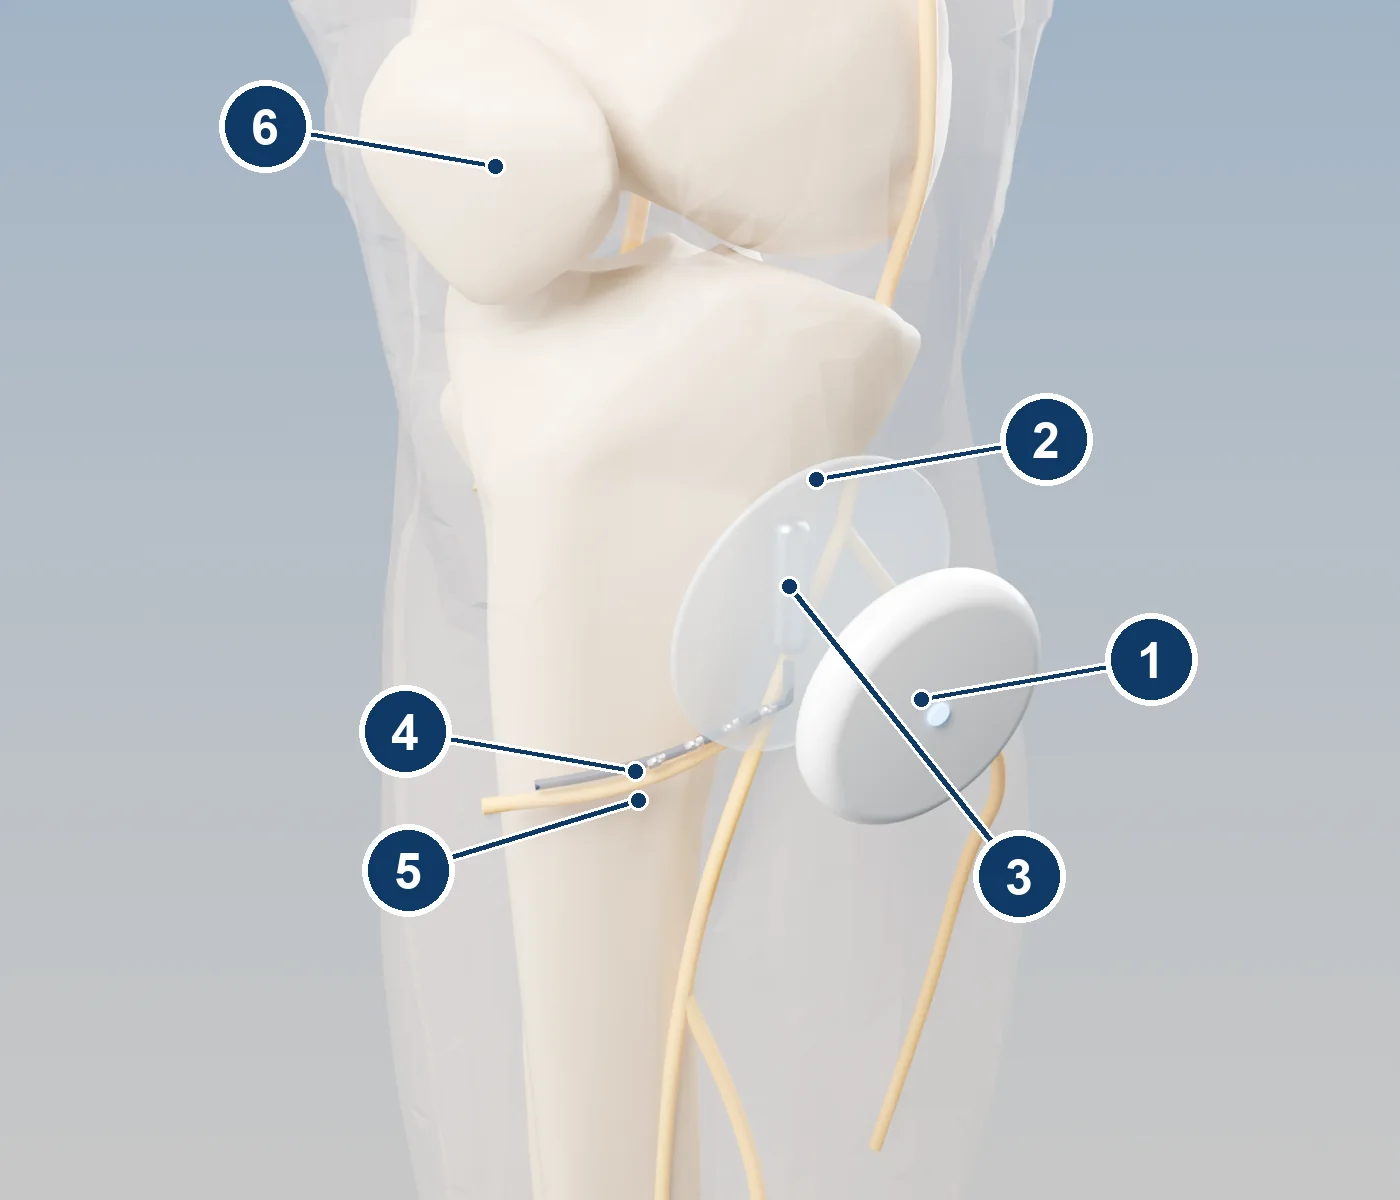
- 1Therapy disc: the wearable battery and controller
- 2Adhesive clip on the skin that the disc snaps onto
- 3Tiny implanted receiver (micro pulse generator) just under the skin
- 4Thin lead with electrical contacts lying beside the nerve
- 5Target nerve. Here it is the infrapatellar branch of the saphenous nerve, a common source of pain around the knee.
- 6Kneecap (patella)
You wear the disc when you want stimulation and can take it off for swimming, showering, or close-fitting clothes. These systems usually come with two discs, so one charges while you wear the other.
Where it is used
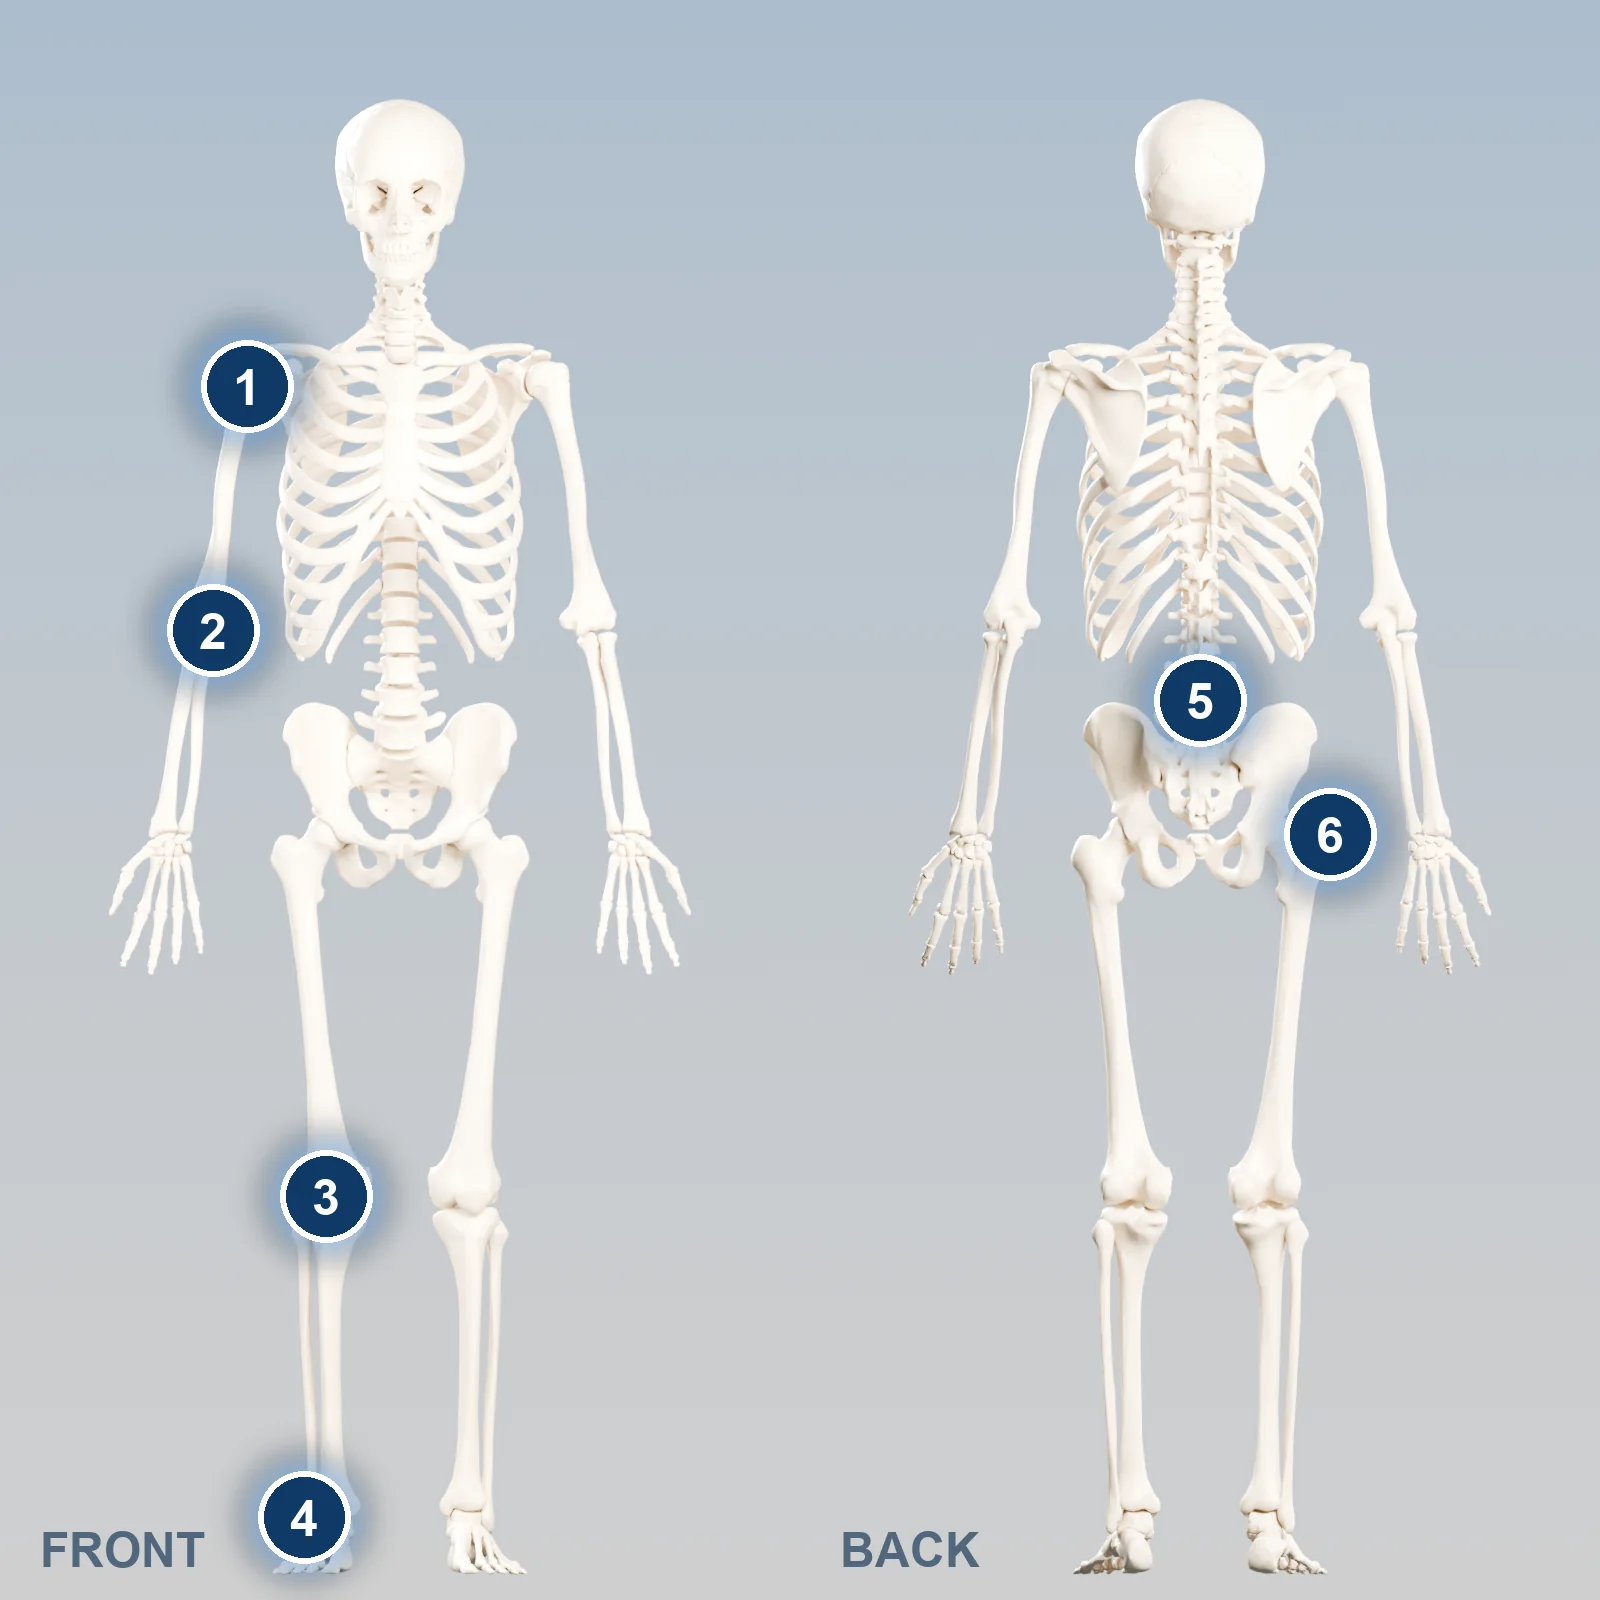
- 1Shoulder
- 2Arm and elbow
- 3Knee
- 4Foot and ankle
- 5Low back
- 6Buttock and hip
Step by step
Evaluation
An exam and review of your imaging and past treatments. Often a diagnostic nerve block (a numbing injection) is used to confirm that the target nerve is causing your pain.
Wear test (some programs)
Before anything is placed, you may wear a non-working disc and adhesive for several days. This checks whether the position is comfortable with your clothing, sleep, and work.
Trial placement
Through a needle, and guided by ultrasound or X-ray, a temporary lead is placed next to the nerve under local numbing, sometimes with light sedation. It connects to an external stimulator. For one system, FDA labeling limits trial devices to 30 days or less.[5]
Trial period
Use it during normal life and keep the diary. As with spinal cord stimulation, the usual target is at least 50% less pain along with better activity and sleep.[3]
Permanent placement
If the trial helps, a minimally invasive outpatient procedure places one or two leads and the small implanted receiver or battery. You are shown how to use the app or remote.
Tune-ups and rehab
Follow-up visits adjust the settings. Keep up your exercise program. As pain eases, it is the best time to rebuild strength and movement.
During the trial
Do
- Use the stimulator during normal activities and try the things pain has stopped you doing
- Rate your pain 2–3 times a day in the diary
- Keep the dressing clean and dry
- Check the skin under any adhesive each day
- Call with questions or if the stimulation changes suddenly
Avoid
- Getting the trial dressing wet unless you have been told it is OK
- Strenuous or repetitive movement of the treated area, which can shift the lead
- Pulling on the external wire or changing the dressing yourself
- Hot tubs, pools, and baths during the trial
Living with a PNS system
Showers, swimming, and clothing
With a wearable-powered system, you take the disc off for water and tight clothing, and put it back on the clip afterward. Fully implanted systems have no external part once healed.
Charging
Wearable discs are swapped and recharged. Fully implanted batteries may need recharging through the skin, or replacement after some years. Ask how often your system needs attention.
MRI scans
Several PNS systems are labeled “MR Conditional”, which means an MRI is possible only under specific conditions. Always tell the MRI team and carry your device card.
Airport security, other devices, diathermy
Carry your device card for security screening. Tell every clinician you have a stimulator. Pacemakers and defibrillators need coordination between teams, and deep-heat therapy (diathermy) should be avoided unless your device labeling says otherwise.
What the research shows
The largest randomized trial of a wearable-powered PNS system is the COMFORT study. Patients with chronic nerve pain in the low back, shoulder, knee, or foot and ankle were assigned to PNS plus usual care or usual care alone.[1],[3]
At 3 months
had at least 50% less pain with PNS, compared with 3% on usual care alone. Average pain fell 67% with PNS versus 6% without.
Relief held up at one year
of PNS patients were still responders at 12 months, with a 69% average pain reduction. The study continues to 3 years.
Comfort of the wearable
of patients found the external disc comfortable to wear. No serious device-related adverse effects were reported through 12 months.
National consensus guideline
A multidisciplinary panel from the American Society of Pain and Neuroscience reviewed the evidence and issued graded recommendations for when PNS should be used.
How to read these results
COMFORT was paid for by the device manufacturer. It was not blinded: the comparison group knew they were not receiving a device, and no sham device was used. Only people who passed the trial went on to a permanent implant. Results beyond one year are still being collected. These are encouraging numbers for carefully selected patients, not a guarantee.
Risks and side effects
Serious complications are uncommon. The most frequent problems are related to the hardware.[6]
- Lead movement away from the nerve, which can reduce relief and may need reprogramming or repositioning
- Infection at the lead or implant site, which sometimes requires removal
- Skin irritation from adhesive patches
- Soreness at the implant site, or stimulation that feels uncomfortable
- Irritation of the nerve itself
- Device malfunction, or the need for another procedure
- Relief that fades over time
Call your care team right away if you have
- Fever over 101°F (38.3°C), or chills
- Redness, warmth, swelling, or drainage at the lead or implant site
- A rash or blistering under the adhesive that is getting worse
- New numbness or weakness in the treated limb
- Stimulation that suddenly becomes painful. Remove the disc or turn it off, then call.
Questions to bring to your visit
- Which nerve do you think is causing my pain, and how will we confirm it?
- Which type of PNS system do you recommend: wearable-powered, fully implanted, or temporary?
- How long will my trial last, and what counts as success?
- Where exactly would the lead and receiver go? Will it interfere with my work, sleep, or sports?
- Can I have MRI scans with this system?
- What will my insurance cover?
Trial diary
Rate your pain from 0 (none) to 10 (worst imaginable). Note the program or setting you used.
| Day | Pain (morning) | Pain (evening) | Activities I tried | Hours slept | Pain medicine taken | Setting / notes |
|---|---|---|---|---|---|---|
| Before | ||||||
| 1 | ||||||
| 2 | ||||||
| 3 | ||||||
| 4 | ||||||
| 5 | ||||||
| 6 | ||||||
| 7 |
References
- Hatheway J, et al. Clinical study of a micro-implantable pulse generator for the treatment of peripheral neuropathic pain: 3-month and 6-month results from the COMFORT randomised controlled trial. Regional Anesthesia & Pain Medicine. 2025;50:561-567. Sponsored by the device manufacturer. doi.org/10.1136/rapm-2023-105264
- Hatheway J, et al. Clinical study of a micro-implantable pulse generator for the treatment of peripheral neuropathic pain: 12-month results from the COMFORT randomized controlled trial. Regional Anesthesia & Pain Medicine. 2026;51:278-284. Sponsored by the device manufacturer. doi.org/10.1136/rapm-2024-106099
- Hatheway J, et al. Design of a multicenter, randomized controlled trial for the treatment of peripheral neuropathic pain (COMFORT study) with a micro-implantable pulse generator. Journal of Pain Research. 2024;17:2891-2901. doi.org/10.2147/JPR.S460563
- Latif U, et al. Consensus guidelines for the use of peripheral nerve stimulation in the treatment of chronic pain and neurological diseases: a NEURON project from the American Society of Pain and Neuroscience. Journal of Pain Research. 2025;18:5949-5990. doi.org/10.2147/JPR.S537222
- U.S. Food and Drug Administration. 510(k) K232415, Nalu Neurostimulation System: indications for use (peripheral nerve stimulation), August 2024. www.accessdata.fda.gov/cdrh_docs/pdf23/K232415.pdf
- Eldabe S, Buchser E, Duarte RV. Complications of spinal cord stimulation and peripheral nerve stimulation techniques: a review of the literature. Pain Medicine. 2016;17:325-336. doi.org/10.1093/pm/pnv025
Related guides
About this page. This guide is general education written for patients. It does not replace advice from your own doctor, and results differ from person to person. Numbers quoted come from the published studies listed in the references; many large device studies are funded by the companies that make the devices, which we note where it applies.
Brand names that appear here are trademarks of their owners. This page is independent: it was not produced, paid for, or reviewed by any device manufacturer.
3D illustrations were rendered for this site from the open anatomy models of Z-Anatomy and BodyParts3D (© The Database Center for Life Science, CC BY-SA 2.1 JP; Z-Anatomy, CC BY-SA 4.0). Device hardware is a generic representation, not any specific product. The illustrations are shared under CC BY-SA 4.0.
Last reviewed: September 2026. If you have urgent symptoms, call your care team or 911.